Prescribe with the guardrails on
One active medication list on the shared care record, checked as it is written. Interaction, allergy, dose and duplicate checks happen at the moment of prescribing, and reconciliation when a person moves between settings, into hospital or home again, is drafted from the current list and confirmed by a clinician.
One list, checked at the point of prescribing
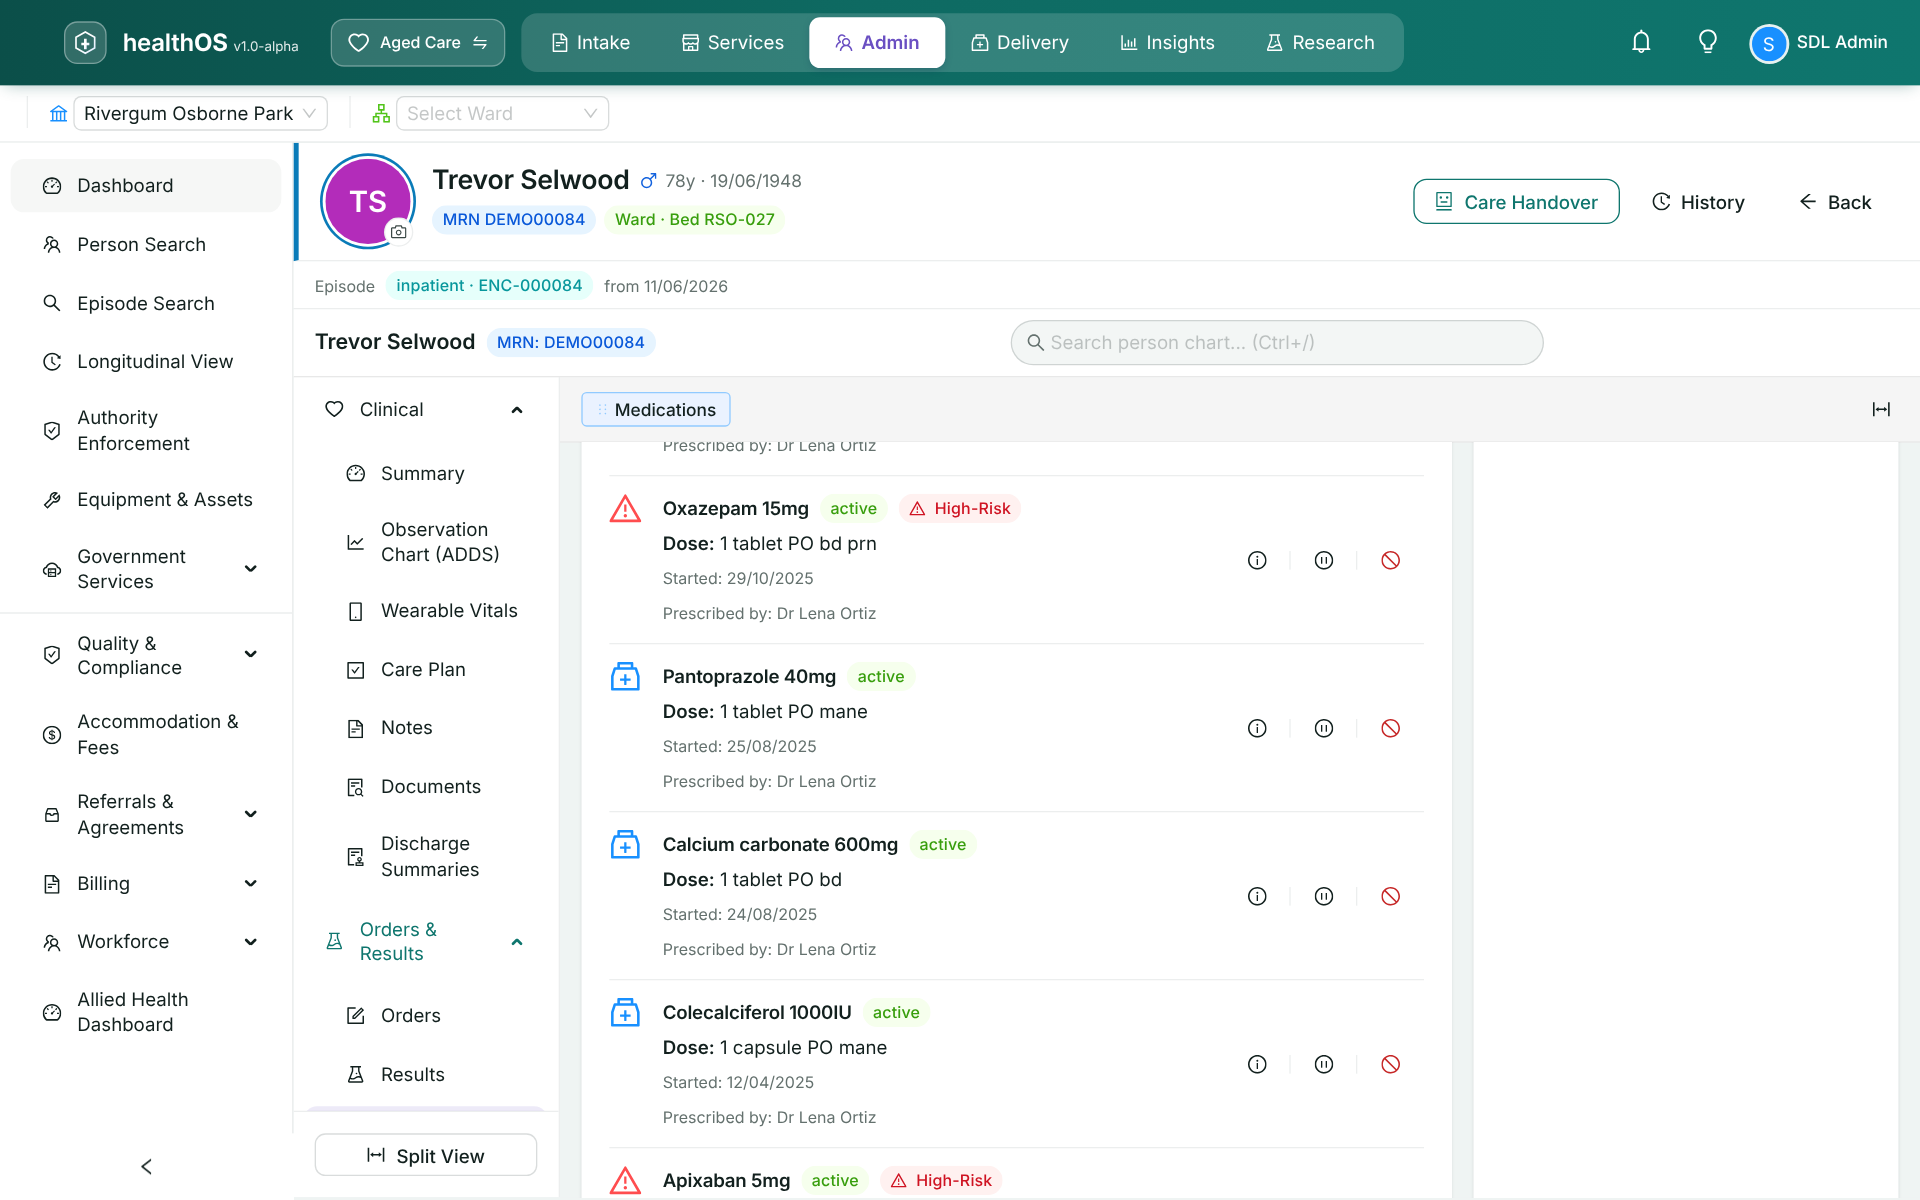
One active list on the person's chart
Medication safety is a property of the workflow, so the checks happen while the script is being written, on the same record everything else reads. The person's chart holds one active medication list with stop, hold and resume, and PRN medications flagged with their reason. Each order shows its dose and prescriber, and high-risk medicines such as anticoagulants and benzodiazepines are flagged on the list.
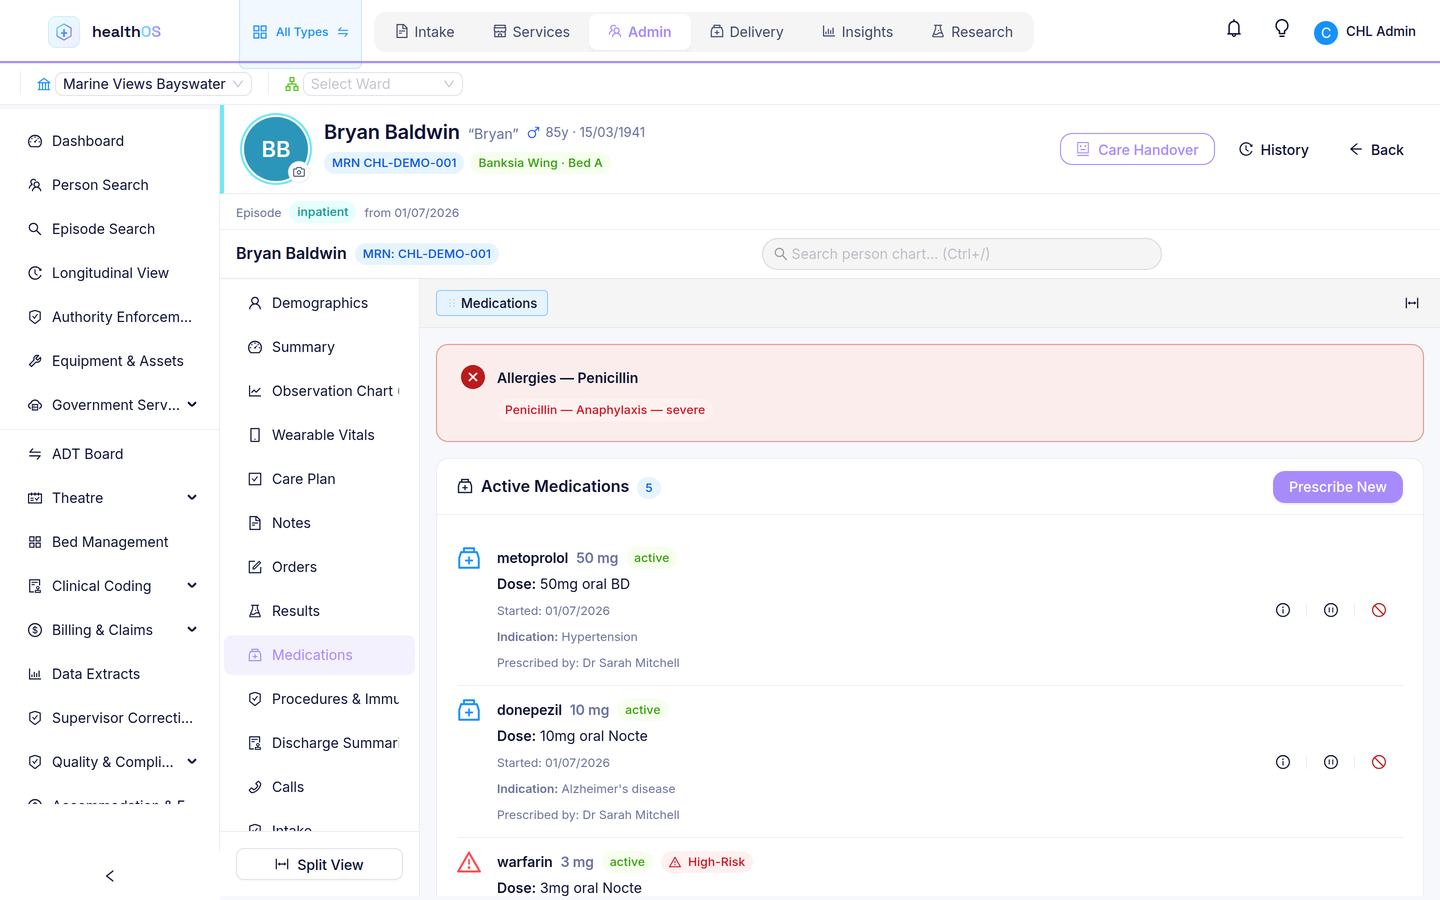
The prescription that argues back
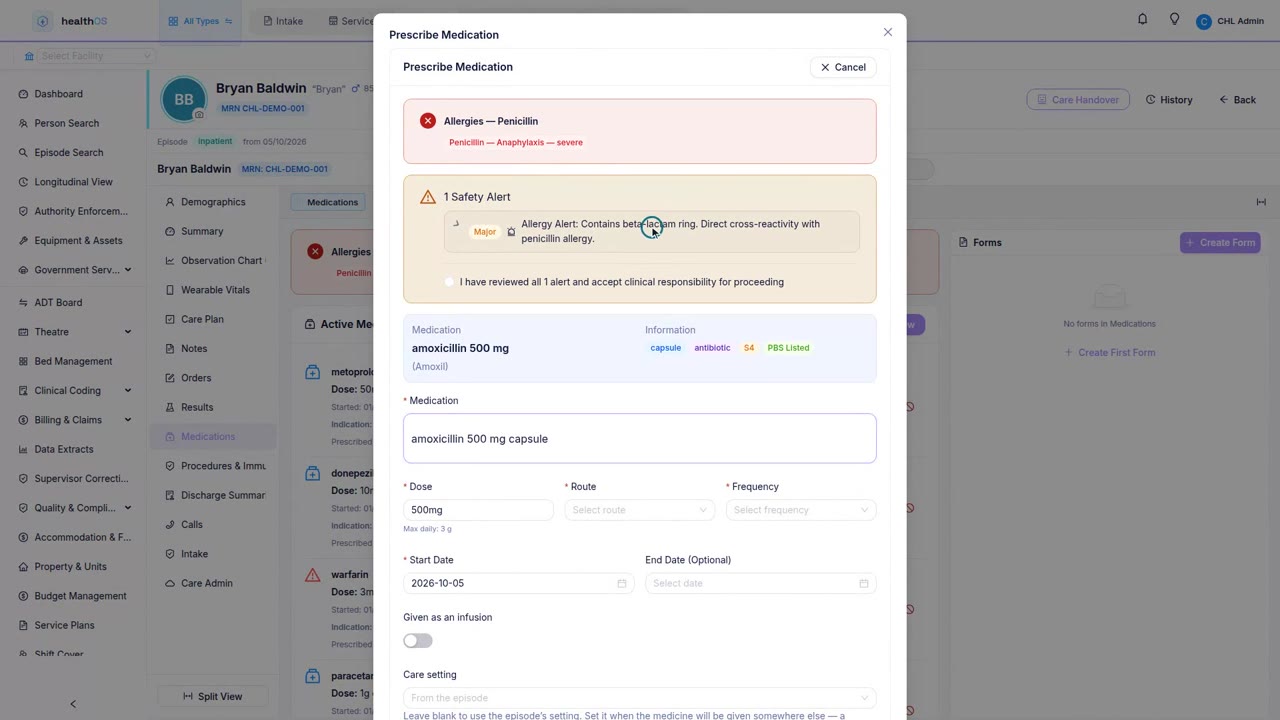
Safety checks run while the script is still being written. A contraindicated combination stops the prescription outright, and lesser warnings have to be acknowledged by the prescriber before it proceeds. The checks are backed by curated Australian interaction data.
- Interaction checking with severities from contraindicated down to minor
- Allergy checks against the allergies already on the person's record
- Doses checked against the maximum daily dose on the formulary
- Duplicate therapy detected across the active list
Every move between settings, list reconciled
Transitions of care are where medication lists break. On a hospital admission or discharge, or a move into residential care, a clinician opens a reconciliation drafted from the person’s current list. When someone comes back with a paper discharge summary, AI reads the scanned copy, de-identified before any model call, and drafts the changes to their list item by item. A clinician confirms every item before anything lands on the list.
- Reconciliation bootstrapped from the current medication list
- Item-level decisions (continue, change or cease), each recorded
- AI extraction is draft-only: a person confirms every line
- Complete-and-review flow with the full trail kept
Coded, so everything downstream works
Medications are stored coded rather than as free text. PBS codes, AMT codes, ATC classes and schedules ride on the formulary, and the list is exposed through FHIR AU Core, the standard health-data format, so claiming, reporting and integration read the same list the clinicians do.
- Common Australian medications seeded with PBS, AMT and ATC coding
- Schedules and maximum daily doses on the formulary
- MedicationRequest read and search on the FHIR AU Core facade
- MedicationDispense export for downstream systems
Pharmacist workbench, eMAR and controlled drugs
These are in development and not yet available.
- The pharmacist workbench: verification queues, clarifications, dispensing and stewardship
- The electronic MAR for medication rounds
- The controlled-drugs register with dual witnessing
The same record, every view
The medication list lives on the care delivery chart. AI handover drafts are grounded in the same record, the deterioration engine reads clinical signals from it, and every change sits on the seven-year audit trail described under security.
See it in action
Related
See prescribing and reconciliation in action
We will walk you through it on real data. Bring questions.